State Policies and Issues
States Can Help Patients Pay Less for Their Medicines
America’s biopharmaceutical companies agree that, for too many Americans, the health care system is not working and needs to change. No one should struggle to afford the medicines they need. Unfortunately, some patients continue to bear more of their medicine costs at the pharmacy counter.
That’s why our companies are advocating for common-sense reforms to make insurance work like insurance and ensure that patients can access and afford the medicines their doctors prescribe.
Unfortunately, some state policy proposals put access to current and future medicines at risk, threaten ongoing research and development into new treatments and cures and jeopardize the high-paying jobs supported by the biopharmaceutical industry.
We believe there is a better way to help patients pay less for their medicines without sacrificing access to medicines, innovation and jobs.
pills in hand
Click the button below to learn more
Alabama
AL
Alaska
AK
Arizona
AZ
Arkansas
AR
California
CA
Colorado
CO
Connecticut
CT
Delaware
DE
District of Columbia
DC
Florida
FL
Georgia
GA
Hawaii
HI
Illinois
IL
Indiana
IN
Iowa
IA
Kansas
KS
Kentucky
KY
Louisiana
LA
Maine
ME
Maryland
MD
Massachusetts
MA
Michigan
MI
Minnesota
MN
Mississippi
MS
Missouri
MO
Montana
MT
Nebraska
NE
Nevada
NV
New Hampshire
NH
New Jersey
NJ
New Mexico
NM
New York
NY
North Carolina
NC
North Dakota
ND
Ohio
OH
Oklahoma
OK
Oregon
OR
Pennsylvania
PA
Puerto Rico
PR
Rhode Island
RI
South Carolina
SC
South Dakota
SD
Tennessee
TN
Texas
TX
Utah
UT
Vermont
VT
Virginia
VA
Washington
WA
West Virginia
WV
Wisconsin
WI
Wyoming
WY
340B
Download the fact sheet on the 340B program in
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles New York 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles California 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Texas 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Alabama 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Alaska 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Arizona 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Arkansas 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Colorado 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Connecticut 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Delaware 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Florida 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Georgia 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Hawaii 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Illinois 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Indiana 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Iowa 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Kansas 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Kentucky 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Louisiana 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Maine 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Maryland 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Massachusetts 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Michigan 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Minnesota 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Mississippi 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Missouri 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Montana 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Nebraska 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Nevada 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles New Hampshire 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles New Jersey 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles New Mexico 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles North Carolina 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles North Dakota 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Ohio 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Oklahoma 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Oregon 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Pennsylvania 2026.pdf
https://cdn.aglty.io/phrma/fact-sheets/340b/2025/Fact Sheet - 340B State Profiles Rhode Island.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles South Carolina 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles South Dakota 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Tennessee 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Utah 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Vermont 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Washington 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles West Virginia 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Wisconsin 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Wyoming 2026.pdf
https://cdn.aglty.io/phrma/Fact Sheet - 340B State Profiles Virginia 2026.pdf
Economic Impact
Download the fact sheet on Economic Impact in
Alabama_Eco Impact One Pager 2022_3.pdf
https://cdn.aglty.io/phrma/fact-sheets/economic-impact/Alaska_Eco Impact One Pager 2022_3.pdf
Arizona_Eco Impact One Pager 2022_3.pdf
Arkansas_Eco Impact One Pager 2022_3.pdf
California_Eco Impact One Pager 2022_2.pdf
Colorado_Eco Impact One Pager 2022_2.pdf
Connecticut_Eco Impact One Pager 2022_3.pdf
Delaware_Eco Impact One Pager 2022_2.pdf
DC_Eco Impact One Pager 2022_2.pdf
Florida_Eco Impact One Pager 2022_2.pdf
Georgia_Eco Impact One Pager 2022_3.pdf
Hawaii_Eco Impact One Pager 2022_2.pdf
Illinois_Eco Impact One Pager 2022_3.pdf
Indiana_Eco Impact One Pager 2022_2.pdf
Iowa_Eco Impact One Pager 2022_2.pdf
Kansas_Eco Impact One Pager 2022_2.pdf
Kentucky_Eco Impact One Pager 2022_3.pdf
Louisiana_Eco Impact One Pager 2022_2.pdf
Maine_Eco Impact One Pager 2022_2.pdf
Maryland_Eco Impact One Pager 2022_2.pdf
Massachusetts_Eco Impact One Pager 2022_3.pdf
Michigan_Eco Impact One Pager 2022_2.pdf
Minnesota_Eco Impact One Pager 2022_2.pdf
Mississippi_Eco Impact One Pager 2022_2.pdf
Missouri_Eco Impact One Pager 2022_2.pdf
Montana_Eco Impact One Pager 2022_2.pdf
Nebraska_Eco Impact One Pager 2022_3.pdf
Nevada_Eco Impact One Pager 2022_2.pdf
New Hampshire_Eco Impact One Pager 2022_2.pdf
New Jersey_Eco Impact One Pager 2022_2.pdf
New Mexico_Eco Impact One Pager 2022_2.pdf
New York_Eco Impact One Pager 2022_2.pdf
North Carolina_Eco Impact One Pager 2022_2.pdf
North Dakota_Eco Impact One Pager 2022_2.pdf
Ohio_Eco Impact One Pager 2022_2.pdf
Oklahoma_Eco Impact One Pager 2022_3.pdf
Oregon_Eco Impact One Pager 2022_2.pdf
Pennsylvania_Eco Impact One Pager 2022_3.pdf
Puerto Rico_Eco Impact One Pager 2022_2.pdf
Rhode Island_Eco Impact One Pager 2022_3.pdf
Tennessee_Eco Impact One Pager 2022_3.pdf
Texas_Eco Impact One Pager 2022_2.pdf
Utah_Eco Impact One Pager 2022_2.pdf
Vermont_Eco Impact One Pager 2022_2.pdf
Virginia_Eco Impact One Pager 2022_3.pdf
Washington_Eco Impact One Pager 2022_2.pdf
West Virginia_Eco Impact One Pager 2022_2.pdf
Wisconsin_Eco Impact One Pager 2022_2.pdf
STEM
Click the button below to download a PDF for STEM in
PhRMA State Fact Sheets - Alabama.pdf
PhRMA State Fact Sheets - Alaska.pdf
https://cdn.aglty.io/phrma/fact-sheets/stem/PhRMA State Fact Sheets - Arizona.pdf
PhRMA State Fact Sheets - California.pdf
PhRMA State Fact Sheets - Colorado.pdf
https://cdn.aglty.io/phrma/fact-sheets/stem/PhRMA State Fact Sheets - Connecticut.pdf
PhRMA State Fact Sheets - DC.pdf
PhRMA State Fact Sheets - Florida.pdf
PhRMA State Fact Sheets - Georgia.pdf
PhRMA State Fact Sheets - Hawaii.pdf
PhRMA State Fact Sheets - Illinois.pdf
PhRMA State Fact Sheets - Indiana.pdf
PhRMA State Fact Sheets - Iowa.pdf
PhRMA State Fact Sheets - Kansas.pdf
https://cdn.aglty.io/phrma/fact-sheets/stem/PhRMA State Fact Sheets - Kentucky.pdf
PhRMA State Fact Sheets - Louisiana.pdf
PhRMA State Fact Sheets - Maine.pdf
PhRMA State Fact Sheets - Maryland.pdf
PhRMA State Fact Sheets - Massachusetts.pdf
PhRMA State Fact Sheets - Michigan.pdf
PhRMA State Fact Sheets - Minnesota.pdf
PhRMA State Fact Sheets - Mississippi.pdf
PhRMA State Fact Sheets - Missouri.pdf
PhRMA State Fact Sheets - Montana.pdf
PhRMA State Fact Sheets - Nebraska.pdf
PhRMA State Fact Sheets - Nevada.pdf
PhRMA State Fact Sheets - New Hampshire.pdf
PhRMA State Fact Sheets - New Jersey.pdf
PhRMA State Fact Sheets - New Mexico.pdf
PhRMA State Fact Sheets - New York.pdf
PhRMA State Fact Sheets - North Carolina.pdf
PhRMA State Fact Sheets - North Dakota.pdf
PhRMA State Fact Sheets - Ohio.pdf
PhRMA State Fact Sheets - Oklahoma.pdf
PhRMA State Fact Sheets - Oregon.pdf
PhRMA State Fact Sheets - Pennsylvania.pdf
PhRMA State Fact Sheets - Puerto Rico.pdf
PhRMA State Fact Sheets - Rhode Island.pdf
PhRMA State Fact Sheets - South Carolina.pdf
PhRMA State Fact Sheets - South Dakota.pdf
PhRMA State Fact Sheets - Tennessee.pdf
PhRMA State Fact Sheets - Texas.pdf
PhRMA State Fact Sheets - Utah.pdf
PhRMA State Fact Sheets - Vermont.pdf
https://cdn.aglty.io/phrma/fact-sheets/stem/PhRMA State Fact Sheets - Virginia.pdf
PhRMA State Fact Sheets - Washington.pdf
PhRMA State Fact Sheets - West Virginia.pdf
PhRMA State Fact Sheets - Wisconsin.pdf
PhRMA State Fact Sheets - Wyoming.pdf
Programs and Initiatives
Download the sheet on Programs and Initiatives in
Clinical Trials
Download the fact sheet on Clinical Trials in
State Policy Solutions
Share the Savings
Share the savings
On average, more than half of spending on brand medicines goes to health insurers, PBMs, the government and others, not the manufacturer that researched and developed the medicine. However, patients often do not benefit from these significant discounts in the form of lower out-of-pocket costs for their medicines.
That’s not right, and it needs to change.
If insurance companies and middlemen don’t pay the full price for medicines, patients shouldn’t have to either. These rebates and discounts should be directly shared with patients.
Make Insurance Work
Make insurance work
Many patients who have relied on patient assistance to access their medicines have no idea that health insurers and PBMs are engaging in practices that can make it harder or impossible for patients to get important treatments for chronic illnesses. This can result in confusion, inconsistency, and unpleasant surprises at the pharmacy counter.
We need to end this practice so that patients are getting the full benefit of programs meant to help them access their medicines.
rx icon
Cost Sharing Solutions
Offer lower, more predictable cost sharing options
Actual spending on medicines is growing at the slowest rate in years. Unfortunately, it doesn’t feel that way for patients. Insurers are increasingly using high deductibles and coinsurance that result in patients paying more for certain medicines out of pocket. Patients should have more choices when it comes to their medicine coverage.
Every state should require health insurers to offer at least some health plan options that exclude medicines from the deductible and offer set copay amounts instead of forcing patients to pay an amount based on the full list price of their medicines.
sharing icon
Cover Medicines from Day One
Cover medicines from day one
Insurers increasingly require patients to pay high deductibles before receiving coverage of their medicines. This can lead to patients rationing or not taking their medicines, which can result in devastating consequences to their health.
Policymakers can help patients from day one by requiring all plans to cover certain medications used to treat chronic conditions with no deductible.
Additionally, insurers should be mandated to offer some plans that cover all medicines from day one.
doctor icon
Cap Patient Cost Sharing
Cap patient cost sharing
Many commercially insured patients are being exposed to high out-of-pocket costs due to increasing use of deductibles and coinsurance. High cost sharing is a barrier to prescription medicine access, especially for patients with chronic, disabling or life-threatening conditions, who shoulder the largest share of the burden.
Cost sharing should not be so burdensome that it prevents patients with insurance from accessing necessary prescription medicines.
sharing icon
Stop Gaming the System
Stop PBMs from "gaming the system"
Health insurance companies use middlemen called pharmacy benefit managers, or PBMs, to negotiate prescription drug prices and develop formularies that determine what medicines people can get and how much they must pay.
system icon
Hold PBMs Accountable
Hold PBMs accountable under state law
Health insurance companies use middlemen called pharmacy benefit managers, or PBMs, to negotiate prescription drug prices and develop formularies that determine what medicines people can get and how much they must pay. PBMs are supposed to help lower costs for medicines, but they often enrich themselves over the interests of patients and their health plan clients.
accountable icon
State Policy Concerns
Government Price Setting
Government price-setting policies come in a variety of forms, but they all lead to the government inserting itself between patients and doctors, threatening access to treatments and chilling research and development of new medicines. In fact, in other countries that have resorted to government price setting, patients have access to fewer new medicines and wait longer to get the medicines they need. Instead of pursuing proposals that could hurt patients and cripple innovation, we need policies that protect access to treatments and make medicines more affordable.
Prescription drug affordability boards are just one form of government price setting policy we’re seeing pop up in states around the country. These proposals would give bureaucrats the power to arbitrarily set medication prices in a given state. As a result, decisions about medicines would be a part of a political process that changes with elections and the whims of politicians.
Under this policy, the state would evaluate whether certain medicines and treatments are “worth” paying for, meaning the state’s bureaucracy could come between patients and the treatments their doctors prescribe. This spells disaster for patients as they could face barriers to obtaining life-saving medication.
people in suits listening
340B
Big tax-exempt hospitals and clinics abuse a little-known federal program to charge huge markups on medicines, sometimes 1,000% or more, to boost their profits, while they pass the bill to patients, taxpayers and employers through higher drug costs. They get away with this by exploiting, sometimes illegally, the 340B hospital markup program. This government program was created in 1992 to help patients access more affordable medicines. Today, the 340B program has become less about patients and more about boosting the bottom lines of hospitals and for-profit pharmacies.
man reading prescription on bottle
Related Resources
Insurers are blaming medicines for premium hikes in Massachusetts. The state's own data suggests otherwise.
Commercial insurers are seeking double-digit premium increases in Massachusetts and pointing the finger at prescription medicines. But the state’s numbers don't back it up.
Why it matters: When one part of the health care system is singled out as the cost driver, it lets the actual drivers — and the middlemen profiting from the status quo — off the hook. Patients and state policymakers deserve the full picture.
By the numbers:
- Total health care spending in Massachusetts reached roughly $83 billion in 2024, according to the state’s Center for Health Information and Analysis (CHIA).
- Spending on medicines, after rebates and discounts: $12.3 billion — less than 15% of total spending and less than both hospital outpatient and inpatient services alone.
- Hospital spending: $29 billion — more than one-third of all health care spending in the state.
- Rebates and discounts provided by biopharmaceutical companies in Massachusetts totaled more than $4 billion in 2024. For commercial health plans, these rebates lowered what plans paid for medicines by nearly 30%.
Yes, but: Those savings too often do not reach patients. Insurers and pharmacy benefit managers (PBMs) negotiate significant discounts behind the scenes — then can still require patients to pay based on the full price at the pharmacy counter. Coverage on paper does not always mean access in practice.
Between the lines:
The big picture: Insurers and the PBMs they own wield enormous influence over the prescription drug supply chain — deciding what medicines are covered, where patients can fill prescriptions and how much they pay.
The bottom line: If policymakers and stakeholders are serious about lowering costs, they need to fix the real drivers of higher spending – like middlemen who can block access to lower-cost medicines.
Learn more at PhRMA.org/PBMs.
Will May
340B is growing, but it is unclear if Illinois patients benefit
A program distorted: Congress created the federal 340B program in 1992 to help vulnerable and uninsured patients access medicines. What once served fewer than 100 safety-net hospitals is now the second-largest federal prescription drug program—topping $81 billion and serving as a cash cow for large hospital systems, for-profit pharmacies, pharmacy benefit managers (PBMs) and other middlemen.
There is no requirement that hospitals use 340B program profits to help patients afford the medicines they need. Big, tax-exempt hospitals abuse this loophole to buy medicines for as little as a penny and mark them up by 1,000% or more—passing the cost on to patients, employers and taxpayers.
The incomplete picture in Illinois: Illinois tax-exempt hospitals and clinics are exploiting the federal 340B program for profit, but they aren't required to disclose what they earn from 340B markups, where that money goes or how it affects patients, employers and taxpayers.
However, reporting in Crain's Chicago Business describes findings highlighted in a recent Illinois Central Management Services (CMS) memo on the program:
- Illinois hospitals generate more than 2.5x as much in estimated 340B-related profit as they spend on charity care.
- Large 340B hospitals charge roughly 7% more on average than comparable non-340B hospitals, with outpatient prices nearly 20% higher.
- The current program is estimated to cost Illinois employers about $224 million a year.
What Minnesota reveals next door: Minnesota's annual 340B transparency report shows an even clearer picture. Large hospitals, clinics and their for-profit partners generated at least $1.48 billion in net revenue from 340B markups in a single year.
Three things from Minnesota’s report stand out:
- Big hospitals profit more than true safety-net providers. Just four large hospitals in Minnesota captured half of the $1.34 billion that went to 340B covered entities.
- Prescriptions for low-income patients are a key source of 340B profits. $261 million came from markups on prescriptions filled for Medicaid patients in Minnesota—costs borne by taxpayers.
- Middlemen are in on it. Contract pharmacies—often owned by the three largest PBMs—received $120 million from the program in Minnesota alone.
The bottom line: 340B is a hidden tax on Illinois employers, taxpayers and patients—with no way to confirm the program is doing what it was meant to do.
Learn more at PhRMA.org/340B.
Will May
State price-setting boards create more questions than answers
The big picture: States are rolling out complex drug price-setting efforts—but there is no evidence yet that patients are or will save money at the pharmacy counter.
What’s new: Longtime supporters of state government price-setting and prescription drug board members themselves are raising concerns about how these policies are playing out and whether patients will benefit or if such policies will make it harder for patients to get their medicines.
-
State prescription drug board architects are uncertain about workability: “Maureen Hensley-Quinn, Senior Director of Coverage, Cost and Value at the National Academy for State Health Policy, said that even when states successfully cap what health plans pay, the complexity of the rebate system means it isn’t always clear whether those savings reach consumers,” according to Pluribus.
-
Prescription drug board members have echoed similar concerns. Dr. Sayeh Nikpay, vice-chair of the Minnesota prescription drug board, cautioned that lowering prices through upper payment limits (UPLs) would not guarantee affordability: “If you lower costs, there’s nothing to say that insurers aren’t going to increase your cost-sharing in the next year.” (MN prescription drug board meeting, 05/30/2024)
-
Patients have been vocal in their opposition to upper payment limits and government price-setting, like Jennifer Reinhardt, a mother to a child with cystic fibrosis in Colorado, who said that the Colorado prescription drug board is “…an experiment, and it’s really gross that they’re doing it on people who are really sick.” Reinhardt added that “the fact that many rare disease patients are alive today is a testament to the value of these treatments. We shouldn’t be forced to go the extra mile to educate [the board] on the value of a therapy, including its impact on long-term health and well-being. Yet proof of life isn’t always enough –the [board] could still decide that a medicine ‘isn’t worth it’ because it has higher costs and so few people are using it. It’s unkind to put families like mine—and the entire rare disease community—under that kind of stress.”
-
State health officials point to broader supply chain distortions that are impacting prices. Annalisa Steeber, of the Minnesota Department of Health, told Minnesota prescription drug board members that “...[what] patients and payers are paying is significantly higher than the price the manufacturer is setting.” (MN prescription drug board meeting, 07/23/2024)
-
Concerns have grown about advancing UPLs within the supply chain: In their policy recommendations for the 2025 annual legislative report, the Oregon PDAB Vice Chair Amy Burns recommended disbanding the board due to concerns about the board’s effectiveness and broader affordability and access issues. Although the Board did not adopt this recommendation, several board members raised related concerns, including fellow board member John Murray’s assertion that they “don't know how [a UPL’s] gonna ripple through the system. I worry about just attacking one part of the cost of the medication. Without addressing all the other areas where it goes.” (minute 33:30)
The bottom line: State bureaucrats promise savings through government price-setting policies like upper payment limits—but more often deliver more bureaucracy, higher administrative costs and disruptive supply chain impacts, with no clear evidence that patients will pay less.
The remedy: Focus on practical reforms—protect cost-sharing assistance and patient assistance programs, hold health plans and PBMs accountable to protect patients from discriminatory health plan features and ensure negotiated savings reach patients directly at the pharmacy counter.
Learn more at PhRMA.org/States.
Reid Porter
States should avoid repeating the IRA’s price‑setting mistakes
As states debate new proposals to regulate prescription drug prices—such as prescription drug boards or referencing federal or foreign pricing—it’s critical to examine the real-world consequences of government-set prices. These proposals focus narrowly on list prices while ignoring the real drivers of patient costs—insurance design and PBM practices.
Early evidence from the federal Inflation Reduction Act (IRA) offers a clear warning: government price-setting is failing to deliver on its promises to patients while creating new risks to innovation, access, and affordability.
If the goal is truly to help patients, states should learn from the IRA’s missteps—not follow the path of government price-setting.
Three takeaways state leaders should not ignore:
- Patients are paying more and facing fewer choices. Since the IRA was enacted, more Medicare plans have increased utilization management and shifted costs onto patients. Avalere Health’s analyses of 2025 and 2026 Part D plan formularies found Part D plans were tightening access to branded medicines, changes that could translate into fewer therapeutic alternatives within classes that contain drugs with an MFP. Today, roughly two-thirds of Medicare Part D beneficiaries are enrolled in plans that use coinsurance instead of copays, a change that exposes many patients to higher out-of-pocket costs. As a result of these shifts, about 60% of beneficiaries in those plans are projected to pay more for six of the medicines for which Medicare set the prices for 2026, underscoring how the IRA’s pricing changes are already translating into higher cost-sharing for patients.
- Price-setting is shrinking the pipeline of future cures. Government price-setting under the IRA has sent a chilling signal to researchers and investors. Since the IRA’s passage, funding for early-stage research into small molecule medicines (including pills, tablets, capsules and liquids), which are scrutinized for price-setting just 7 years after FDA approval, has dropped by nearly 70%. These treatments are often the backbone of care for conditions like cancer, heart disease and Alzheimer’s—diseases that disproportionately affect seniors. State-level price controls would compound this damage, discouraging the very innovation patients are counting on tomorrow.
- Clinical progress slows when the government dictates prices. Clinical trial activity following the passage of the IRA tells the same story. New trials for small molecule medicines are down roughly 25%, and studies exploring new uses for existing medicines—often where breakthroughs occur—have fallen by as much as 45%. For cancer patients, this is especially concerning: many life-extending therapies are approved years after a drug’s initial launch, just as price controls take effect under the IRA. State price-setting policies risk cutting off progress midstream.
The bottom line
These takeaways are not unique to Medicare price-setting—they are inherent risks of any government price-setting approach. Price-setting creates uncertainty for patients and the supply chain while ignoring the real drivers of costs, such as unchecked PBM practices and excessive hospital markups. Many states are beginning to employ more effective tools, such as requiring health insurance companies and PBMs to share at least part of their negotiated savings with patients at the pharmacy counter, as well as protecting patient assistance and insurance design fixes, to reduce patient costs today without jeopardizing access, competition or innovation. If states want to improve affordability and access, the lesson from the IRA is simple: don’t repeat a policy that’s already failing patients.
Learn more at PhRMA.org/States.
Reid Porter
Virginia should be cautious about importing federal price-setting mechanisms
PhRMA believes that discussions about the affordability of medicines are important and that these discussions should consider the entire drug supply chain. Transparency and accountability across the supply chain are important so that policymakers and patients can understand whether savings provided by manufacturers to insurers and pharmacy benefit managers (PBMs) are reaching patients at the pharmacy counter. However, recent price-setting legislation in Virginia could limit prescription options by failing to recognize the complexity of a pharmaceutical supply chain that functions nationally, not state by state, and by targeting only manufacturers.
Here are three reasons price-setting approaches are not right for Virginia:
- Price-setting proposals fail to address the real drivers of access and affordability issues.
-
Regardless of how these proposals are designed, they continue to focus narrowly on the list price of drugs while ignoring the flaws in our system that allow roughly half of every dollar spent on medicines to flow to entities that didn’t make them.
-
Middlemen, such as PBMs and insurers, decide which medicines patients can access, what hoops they need to jump through and how much they pay out of pocket — often failing to pass savings from rebates, discounts and other price concessions directly to patients.
-
Focusing on the list price of drugs alone fails to confront these underlying dynamics and does little to lower costs for patients at the pharmacy counter.
-
- Price-setting mechanisms like the IRA can have a negative impact on patients.
-
The reality of the Inflation Reduction Act’s price-setting measure, which this Virginia legislation attempts to import, is that most Medicare Part D patients are not expected to experience any cost savings from price setting. In fact, recent research shows that 60% of beneficiaries are projected to face higher cost-sharing after reaching the deductible and before the maximum out-of-pocket cap than they would have faced in 2023 for six of the drugs price-set for 2026.
-
Adopting the IRA’s price-setting policies will not address the real drivers of rising costs – insurers and PBMs that control insurance benefit design ultimately decide what a patient pays at the pharmacy counter.
-
States like Virginia are likely to have difficulty extending the IRA’s price control to non-Medicare markets since that price control was designed specifically for Medicare. This raises serious doubts about how a state version could be implemented in Virginia given that the prescription drug market and distribution strategies function nationally.
-
- Innovation pays the price.
-
Early lessons from the Inflation Reduction Act suggest that government price-setting can reduce treatment options and reshape investment decisions.
-
An analysis of early-stage venture capital investment shows funding for small molecule medicines declined by roughly 70% following the IRA’s introduction — a troubling signal for future innovation.
-
Bottom line: Patients deserve real solutions
Patients need lower out-of-pocket costs without sacrificing access, choice or innovation.
Virginia should learn from the federal price-setting experience and focus instead on protecting patient access and affordability by addressing the abusive practices of insurers and PBMs.
Will May
New report from Minnesota: 340B is generating billions for big hospitals
Large hospitals, clinics and their for-profit partners in Minnesota generated at least $1.34 billion in net revenue from 340B medicine markups in 2024, according to the Minnesota Department of Health’s annual 340B transparency report.
Despite the profits reaped by tax-exempt hospitals, extensive independent research shows the 340B program often fails to lower costs or improve access for patients and instead drives higher costs for everyone.
Here are four key takeaways from the report:
- 340B is a hospital markup program. For the second consecutive reporting year, MDH data provide additional evidence that the 340B hospital markup program is being abused by tax-exempt hospital systems and for-profit middlemen to generate revenue at the expense of patients, employers and taxpayers.
- Big hospitals profit at the expense of true safety net providers. Just four large hospitals captured half of the $1.34 billion in 340B program profits. This illustrates how large hospital systems receive a disproportionate share of program profits in comparison to smaller clinics and hospitals.
- Prescriptions for low‑income patients are a key source of 340B profits. Nearly $261 million in 340B net revenue statewide came from markups on prescriptions filled for Medicaid patients—underscoring how the program is generating revenue from medicines for low‑income patients.
- Middlemen are in on the shell game. Thanks largely to vertical integration and consolidation, Pharmacy Benefit Managers (PBMs) have no shortage of ways to profit off medicines, and 340B is just another example. In Minnesota alone, contract pharmacies which are often owned by the three largest PBMs, received $120 million from the 340B program and roughly only half of those were in-state pharmacies.
Where is the money going? With hospitals in one state alone generating billions of dollars in net revenue each year from the program, it begs the question: where is the money going?
Since there are no guardrails on how program profits are used, and the program lacks transparency, it’s hard to say exactly. However, if you look at the receipts, many of the hospitals profiting most are spending money in egregious ways, without any evidence that patients benefit.
Bottom Line: If policymakers want to lower health care costs they must fix the federal 340B program. Until then, hospitals will continue to exploit the program for profit at the expense of patients, taxpayers and employers.
Reid Porter
50-state poll says Americans are concerned that hospital markups hurt patients
Across the nation, voters are frustrated with hospital markups, drug middlemen practices and lack of transparency that make it harder to access medicines.
In new polling with Morning Consult, 20,012 Americans across all 50 states and 435 congressional districts were surveyed to discover how widespread frustrations with hospital systems and other drug middlemen have become. Americans are tired of unfair and unaffordable hospital practices, especially aggressive markups. Nine in 10 Americans (87%) are concerned about hospitals’ price markups on medicines. This includes 88% of Republicans and 90% of Democrats concerned.
Too often, lifesaving medicines purchased by hospitals at reduced prices are then resold to patients at massive markups. The majority of Americans are concerned about these hospital medicine markup practices, as well as other hospital antics meant to boost profits at the expense of patients.
The majority of hospitals now participate in a little-known federal program called 340B. Congress created 340B in 1992 to help patients access more affordable medicines. Today, the program has become less about low-income patients and more about boosting the bottom lines of large hospital systems and for-profit pharmacies. As Americans learn about the 340B program, they are highly concerned about specific ways hospitals are exploiting it for profit. Key drivers of concern include:
- Hospitals buying medicine for as little as a penny and marking it up by thousands of dollars (84%)
- 340B hospitals pursuing aggressive debt collection (83%)
- 340B program driving up taxpayer costs - $20 billion in increased costs to Medicaid and Medicare in one year alone (82%)
Frustrations with drug middleman practices drive call for solutions. It’s not surprising that Americans want reforms that prioritize patient savings and increase transparency. 83% agree that policymakers should focus on cracking down on the abusive practices of health insurance companies and middlemen.
Policymakers that want to offer Americans some relief from health care costs and access barriers have multiple pathways supported by the public. For example, 81% of Americans are concerned about the lack of transparency and accountability in how pharmacy benefit manager (PBM) practices affect patients’ access to care. To address these issues, Americans favor PBM reforms that prioritize patient savings and increase transparency:
- 80% favor requiring insurance companies and PBMs to pass rebates/discounts directly to patients.
- 77% favor caps on out-of-pocket prescription costs.
- 76% favor requiring health insurance companies and their PBMs to count patient assistance received from drug companies, such as copay coupons, toward the deductible.
The calls for federal reform are loud and clear from voters in all 50 states, and policymakers must heed these concerns and finally address abusive PBM practices and 340B hospital markups, to help ensure that the 340B program actually benefits patients as intended.
Learn more at PhRMA.org/340B, PhRMA.org/PBMs or PhRMA.org/States.
Cynthia Hicks
California’s landmark PBM crackdown: A wake-up call for reform
Driving the news: California just passed the nation’s most sweeping pharmacy benefit manager (PBM) reform law – taking direct aim at years of hidden fees, drug markups, and patient harm.
Why it matters: California’s bipartisan move sends a powerful signal that states can end opaque PBM practices that have quietly siphoned billions from patients and health systems.
- PBMs have long claimed to lower drug costs while layering on hidden fees.
- California’s new law flips the script – ushering in transparency and accountability.
- Patients could finally see real savings at the pharmacy counter.
What’s in the California PBM reform law?
- Flat-fee compensation for PBMs from payers – PBMs can no longer require payments from payers be tied to drug prices.
- Ban on spread pricing and patient steering.
- Transparency in fee structures.
- Rebates from drugmakers must go to payers – not PBMs.
By the numbers
- 3 PBMs control 70% of national specialty drug revenue.
- $7.3B in excess revenue from specialty drug markups (2017–2022).
- Medicare patients paid 4x more than insurers for 79 of 100 highly rebated drugs.
- 30% of Americans now ration medications due to cost.
- Out-of-pocket costs have risen 5.8% annually since 2016 – despite flat negotiated prices.
- 6 PBMs handle 94% of all prescription claims nationwide.
Collateral Damages: Patients and their community pharmacies are losing out. PBM practices are creating pharmacy deserts nationwide as independent pharmacies are closing fast – just look at the well documented underserved areas in California, Minnesota and Massachusetts.
Americans want action: Voters are demanding patient-centered solutions to lower drug costs and ensure savings reach patients. California’s law proves that comprehensive, bipartisan PBM reform is possible. States can ensure that rebates reach patients directly at the pharmacy counter and enact compensation reform to curb abuses by middlemen throughout the supply chain.

The Bottom Line: PBMs have been called “modern gangsters” by state officials and there’s little to suggest that their business practices will change. Mounting evidence shows that middlemen and other entities that don’t make medicines are using medicines as a profit center at the expense of patients.
California is the latest state to push back on PBM profiteering, and momentum is growing across the country with bipartisan support. It’s clear that without reforms, plans and PBMs are free to continue these abusive practices, leaving patients to navigate an increasingly complex and costly system to get their medicines.
Learn more at PhRMA.org/PBMs.
Reid Porter
Why states struggle to deliver savings: Middlemen and 340B siphon dollars from patients and states
State and federal investigations have shown 340B is often exploited for profit, yet some states have passed laws attempting to protect these practices from oversight. They have repeatedly found evidence that large hospital systems participating in 340B charge more for services or prescription drugs than non-340B hospitals.
For-profit third-party administrators and pharmacies that contract with hospitals are also making huge amounts off the program. Only in the U.S. do entities that do not make brand medicines—like PBMs, insurers and the 340B program—receive half of every dollar spent on them.
By the Numbers:
- 84.8% higher markups: 340B hospitals in North Carolina billed the State Health Plan nearly 85% more than non-340B hospitals, with a majority of 340B hospitals billing state employees triple their acquisition cost for cancer drugs.
- $36 billion extra employer spending: Large 340B hospitals charged nearly 20% more for outpatient procedures compared to similarly sized non-340B hospitals, resulting in approximately $36 billion annually in extra employer spending.
- $1.6 billion profits for one middleman: CVS subsidiary Wellpartner, acting as a third-party administrator, profited from 340B (2019–2023).
- $2.3 billion off the backs of state governments: Because of 340B hospitals, states collectively lost out on over $2 billion in in Medicaid rebates, with some states forgoing between $170 to $265 million.
- Zero evidence 340B markups support underserved patients: Data from Minnesota shows that the program mostly benefits large institutions and for-profit middlemen, with no evidence these entities use 340B-generated profits to help vulnerable patients.
Why It Matters:
The federal 340B hospital markup program—along with PBMs, insurers and other middlemen—is a leading driver of medicine spending in the United States. Yet some states have created boards focused on approaches that overlook these drivers. As Dr. Sayeh Nikpay, a member of Minnesota’s prescription drug board, noted in a recent Health Affairs piece, hospital markups on 340B drugs “may come at the cost of patient affordability,” highlighting a tension between the 340B program and Minnesota’s board efforts. Dr. Nikpay made this point more directly in her recent presentation to the board:
“I think it needs to be stated that there is this central tension between the objective of the 340B program or covered entities that are participating in the 340B program and what the PDABs would like to do.” – Dr. Nikpay, June 10, 2025
But 340B is only one example of the many complex and interconnected factors affecting affordability. And many of these factors, like 340B, cannot be addressed by prescription drug board-imposed upper payment limits.
In states with these boards, members have acknowledged uncertainty about both their feasibility and the impact of upper payment limits on patients.
“...how our decision is going to lead to a net cost reduction for patients I think is still kind of an unknown for us...” – CO PDAB Member Dr. Amy Guiterrez, July 3, 2024 (56:30 – 56:39)
The Big Picture:
Any state seeking savings in the health care system should fully understand and account for the complex dynamics impacting affordability—including the interplay of 340B hospital markups and PBM abuses—and the role of different supply chain entities in determining what patients pay. Delivering patients real change demands comprehensive reform to curb exploitation by middlemen and federal reform of the 340B program, not government price-setting.
Learn more about how government price-setting can have harmful consequences, without addressing the real drivers of cost at PhRMA.org/PriceSetting.
Reid Porter
Medical innovation takes center stage in state legislatures
Recently, PhRMA had the opportunity to partner with the National Conference of State Legislatures (NCSL) for a panel discussion at their 2025 Legislative Summit in Boston, Massachusetts. The panel discussion centered around groundbreaking U.S. biopharmaceutical innovations, the positive impact for patients globally, and the policies that can nurture and protect them for generations to come.
Nearly all innovative, impactful medicines have one thing in common: They start and end in the states.
States play a critical role in providing an environment where academic institutions, research centers and private companies collaborate. Clinical trials also take place in communities across the country, giving patients access to promising treatments. And, once approved, medicines are delivered back through local doctors, hospitals and pharmacists.
Innovation is deeply human. During the panel, we heard stories about:
- HIV/AIDS: How grassroots care and community models can help bridge trust and connect patients in marginalized communities with innovative treatments.
- Rare disease & NICU care: One panelist shared how access to cutting-edge clinical trials in his home state of Massachusetts saved his premature twins, showing how location and access can mean the difference between life and loss.
- Cancer & beyond: New medicines contributed to 1.3 million fewer cancer deaths (2000–2016). Cardiovascular and mental health therapies are reshaping outcomes for patients nationwide.
Even when a drug doesn’t make it to approval, the search itself strengthens local and state economies:
- The biopharmaceutical sector supports more than 90,000 jobs in Massachusetts.
- North Carolina hosts nearly 800 life sciences companies employing 70,000 people.
- Across the U.S., the biopharmaceutical sector drives $1.6 trillion in economic output with facilities in 48 states.
Bottom line: With the right political environment, states are the perfect place to host collaboration, bring promising treatments to patients through clinical trials, and act as the hub for significant economic and workforce benefits in the process.
Learn more about the panel.
Stami Turk
North Carolina puts patients first with rebate pass-through law
North Carolina has passed legislation (SB 479) that requires pharmacy benefit managers (PBMs) to share manufacturer rebates directly with patients at the pharmacy counter. This bold reform confronts a broken system that has for too long allowed PBM middlemen to use medicines as a profit center, charging billions in rebates and fees with no guarantee they will share those savings with patients.
What you need to know:
- Rebates, discounts, and other price concessions that PBMs and insurers get can lower the net price that they pay for medicines by more than 50%. Yet, PBMs and insurers often charge patients based on the full price, meaning patients can pay more for their medicine than their insurer and PBM.
- PBMs should share these savings on medicines directly with patients at the pharmacy counter and help lower their out-of-pocket costs.
- By demanding rebate pass-through, North Carolina is delivering meaningful relief to the people who need it most.
North Carolina’s legislation will make medicine more affordable and accessible for patients. This action builds on momentum seen in states like Arkansas, West Virginia and Indiana, all of which passed similar “share the savings” reforms.
Bottom line: Transparency and accountability are finally being prioritized over opaque PBM practices that drive up costs for patients and the health system writ large.
Learn more: PhRMA.org/Middlemen
Stami Turk
How the 340B hospital markup program could hurt Michigan patients
As lawmakers in Lansing debate health care legislation, new evidence reveals a staggering—and deeply troubling—reality: big, tax-exempt hospitals in the state are marking up the price of prescription medicines by nearly $10 billion a year. The federal 340B program is running unchecked with limited transparency and accountability, and comprehensive federal reform is needed to stop abuse of the program.
A recent report from the nonpartisan Michigan Health Purchasers Coalition, covered by The Detroit Free Press, found that Michigan hospitals spent roughly $4 billion on prescription drugs in one year, yet billed patients nearly $14 billion for the same medicines.
That’s a markup of nearly $10 billion, with some drug prices inflated by as much as 800%.
Equally alarming, the Free Press was unable to find a single hospital system in Michigan willing to disclose what they charge patients. Patients deserve honest answers and fair pricing. As Michigan lawmakers consider health care proposals, they should:
- Demand real transparency from hospitals. They should disclose the amount they make by marking up prices for prescription drugs.
- Reject misguided 340B legislation that forces manufacturers to sell medicine at steeply reduced prices without ensuring that patients benefit. Policies like this reward opaque systems and undermine patient-centered care. Reject misguided 340B legislation that expands the program by requiring the provision of 340B-priced drugs to all large chain pharmacies that contract with the covered entities.
Congress must fix the federal 340B program. It's time to put patients before profits.
Learn more at PhRMA.org/340B.
Stami Turk
Virginia, Don't Let Politicians Take Away Your Medicine
Making the best decision about which medicines to take should be a decision between patients and their doctors, not unelected bureaucrats. Price-setting boards, such as the prescription drug affordability board (PDAB) being proposed in Virginia, ignore this principle and threaten access to life-saving medicines.
Here’s why:
- It puts bureaucracy over providers: PDABs allow unelected bureaucrats to determine the cost of medicines. This puts the state government between doctors and their patients and risks limiting the treatments patients can access.
- It’s ineffective and costly: States with price-setting boards have spent millions creating their PDABs without seeing savings for patients yet. For example, the Maryland PDAB has cost millions. Established in 2019, the PDAB has not saved a single patient a dime on their medications and has yet to show any evidence of lowering patient costs.
- It’s not a real solution to rising costs: Price setting doesn’t address the root cause of high drug costs—insurers and pharmacy benefit managers (PBMs). They control what patients pay at the pharmacy, often costs for patients and limited access to medications, no matter how prices are set.
- It builds on the IRA’s failed promise: The Inflation Reduction Act (IRA) is proof that government price-setting doesn’t work. These price controls are threatening seniors’ access to medicines they need. In fact, 78% of insurers say they will limit therapeutic options available to Medicare Part D enrollees. This will make it harder for patients to get the medicines they need when they need them.
Patient groups across the country have publicly shared their concern that PDABs may reduce access to medicines. And they’ve been joined by voices across the supply chain including hospitals, insurers, and doctors. These voices expose real and unfortunate potential consequences to government price-setting. Ask patients in Colorado suffering from Cystic Fibrosis who had their vital access to medicines threatened by the PDAB.
The focus should be on real reform, not bureaucratic overreach. Instead of price-setting boards, we need solutions that address systemic issues with insurers and PBMs and improve access to life-saving medicines.
Stami Turk
Man searching something on laptop
7 reasons why states shouldn’t copy the IRA’s price setting mistake
State governments should use the Inflation Reduction Act (IRA) as a cautionary tale: a misguided price setting policy that will lead to higher costs for seniors and people with disabilities while reducing access to innovative treatments. Here are seven ways the IRA has made things worse, and why state leaders shouldn’t copy it:
1. Reduced Access: Government price setting can spur the increased use of health insurer measures designed to keep patients from accessing specific treatments. The majority (78%) of insurers say they expect to limit therapeutic options in their plans in direct response to price setting, a situation that will greatly decrease patients’ options for medicines.
2. No Out-of-pocket Savings: The reality is most Part D patients are not expected to experience any cost savings from price setting. The administration’s estimated savings for patients of $1.5 billion assumes all patients are enrolled in a Part D plan with standard benefit design – but that’s not the case. Only 2% of non-low-income Part D patients are enrolled in the standard benefit. Most beneficiaries taking medicines selected for price setting are in enhanced plans with fixed copays, so they likely won’t see lower out-of-pocket costs. Sound familiar? Not one state prescription price setting board has saved patients any money to date.
3. Ignores Bad Actors: Adopting the IRA’s price-setting policies will do nothing to address the real drivers of rising costs: insurers and pharmacy benefit managers (PBMs) that control insurance benefit design, what hoops patients must jump through to get their medicines and what patients pay at the pharmacy counter. Patients have seen this in the states too: state price setting boards have so far ignored the role of middlemen in the health care system and their control over what patients pay for their medicines.
4. Restricts Innovation: According to economists, the impact on innovation will be significant. Looking at the next several years, Vital Transformations conservatively estimates that as many as 139 medicines are at risk of not being developed as a consequence of the IRA.
5. Creates a Pill Penalty: Seniors who depend on small molecule medicines (simply, medicines that come in pill or capsule form) will find them harder to access in the future. Under the IRA, small molecule medicines can be selected for price setting as early as seven years after the FDA’s initial approval, which is long before the end of the average 13-to-14-year effective patent life. As a result, this “pill penalty” may discourage companies from researching and developing small molecule medicines at all. Looking at the next several years, experts at the University of Chicago estimate the IRA could lead to a $232 billion reduction in R&D for small molecule medicines.
6. De-centers Patient Voices: Patients and doctors’ voices were largely left out of the Centers for Medicare and Medicaid’s (CMS) approach in implementing the IRA’s price setting policies. Patients have already frequently voiced concerns about whether the state’s price setting board is taking their experiences into account, like the Colorado patient below.
"As someone who takes daily medications, this board is of the utmost concern to me. I was staunchly against the implementation of the drug affordability board initially, and I have been continually disappointed by their disregard for patients throughout the implementation process.
"As the [The Denver Gazette] noted, price caps are not a magic wand that instantly reduces costs. Instead, they pose serious threats to medical research and impose long-lasting consequences on our most vulnerable patients. Further, it is absurd to think that an unelected board should have the authority to undermine what medical professionals deem best for their patients. Not only is that a slap in the face to our doctors, but it can cause severe health complications for patients.” Carl Ecklund, letter to the editor, The Denver Gazette
7. Taxpayers foot the bill. The IRA allocated $3 billion to the U.S. Department of Health and Human Services (HHS) to implement the price setting process. Today, states with existing price setting boards have already spent millions of dollars on creating and supporting the boards, without one dollar saved in any state to show for it. How many more taxpayer dollars should go to creating more unelected bureaucratic barriers rather than passing solutions that could save systemic and patient out-of-pocket costs today?
Rather than adopting the misguided policies of the federal government, states should focus on tackling system-wide abuses by insurers and PBMs to ensure patients have consistent and affordable access to medicines.
Reid Porter
7 reasons why states shouldn’t copy the IRA’s price setting mistake
Three ways state drug price setting boards fail patients
State drug price setting boards put politics in between doctors and their patients. Instead of addressing the root cause of affordability and accessibility problems, these bureaucratic proposals are likely to harm patients’ access to care and threaten research and development (R&D) of new medicines. Despite misleading rhetoric, the reality is that state price setting boards:
1. Fail to address drivers of access and affordability challenges.
Over half of every dollar spent on medicines goes to insurers, PBMs and others in the supply chain, and three PBMs control 80% of the national market. These self-serving middlemen employ abusive practices to pad their bottom line by deciding what medications patients receive and what price they pay — repeatedly choosing profits over patients. These middlemen may even divert assistance from manufacturers meant for patients to themselves as profit.
Concerns are mounting around PBMs, from investigations for anticompetitive behavior that illegally distorts the market to hurting consumers and threatening the survival of independent pharmacies, according to a recent report by the U.S. Federal Trade Commission and a U.S. House Committee on Oversight and Accountability investigation.
The bottom line: State drug price setting boards do not fix this broken system, instead turning a blind eye to PBM and insurer practices that drive up costs and create access barriers, like prior authorization.
2. Discourage R&D for crucial lifesaving medications.
Federal price-setting policies are already impacting investment in R&D, increasing the likelihood that these state boards will do the same. In recent comments in the Wall Street Journal from Charles River Laboratories International, which provides drug-development services to pharmaceutical companies, the company cited federal price setting policies in the Inflation Reduction Act as one of the drivers of cuts to R&D by its clients. Those policies have not even fully been implemented yet and they are already having an impact. This should be a massive warning sign to all state governments.
The bottom line: Americans rely on cutting-edge medications to address a wide range of diseases and chronic conditions. Policies like state drug price setting boards, which threaten drug development, put access to future treatment and cures at risk.
3. Have yet to save taxpayers and patients money; but already cost states and taxpayers millions.
States with existing price setting boards have already spent millions of dollars each on creating their board, without one dollar saved to show for it. In fact, these boards are designed to put a state’s fiscal year budget first rather than implementing policies that prioritize patient savings without jeopardizing the research and development of medicines.
The bottom line: State price setting boards not only cost states money, but also, often, taxpayers foot the bill.
Even worse, PDAB members are forging ahead toward price-setting for life-saving medications despite a lack of understanding about how their decisions will function in reality and affect patient access to medicines.
At a meeting earlier this summer in Colorado, board members acknowledged that many unanswered questions remain surrounding the impact and feasibility of their work, and that they themselves don’t know how price setting will impact patients.
“...how our decision is going to lead to a net cost reduction for patients I think is still kind of an unknown for us...” - PDAB Member Dr. Amy Guiterrez (56:30 – 56:39)
In addition, state drug price setting boards lack clear, transparent, and consistent standards and processes; routinely rely on flawed data, rarely provide (see page 2) adequate time for public comment to help inform their decisions; and are not always required to provide clarity regarding their conflicts of interests — or those of the advisors who have shaped the boards — and recusal processes for board members.
It’s clear that state drug price setting boards could hurt the patients they claim to serve. They needlessly risk patient access to medications, could stifle the pipeline of future innovative medicines, and allow PBMs to continue gouging patients at the pharmacy counter. It is critical that these boards tackle the true drivers of increasing drug prices rather than pursuing a politically charged policy that harms and doesn’t help.
Reid Porter
Three ways state drug price setting boards fail patients
Biopharmaceutical industry supports jobs and drives economic growth across the United States
Biopharmaceutical manufacturers change lives with groundbreaking medicines while supporting nearly 5 million U.S. jobs. A new report from TEConomy Partners highlights the positive impacts biopharmaceutical innovation has for state and regional economies in the U.S. In total, 47 states and Puerto Rico are involved in the manufacturing of FDA-approved medicines.

Biopharmaceutical companies and their supply chains are key contributors in supporting jobs and local economies across the country. The analysis shows that industry weathered economic downturns, demonstrating 30 percent growth from 2015 to 2022, providing vital stability to both the production of life saving medicines and to the U.S. and regional economies in which it operates.
Economic Output
- The U.S. biopharmaceutical industry exceeded $800 billion in direct output in 2022 and contributed an additional $850 billion in output through its suppliers and other sectors of the economy, for a total of more than $1.65 trillion. This combined, total output impact represents 3.6 percent of all U.S. output.
- The biopharmaceutical sector and its supply chain generated at least $1 billion in economic output in each of 48 states, as well as Puerto Rico and the District of Columbia.
- California alone generated more than $276 billion in economic output thanks to the biopharmaceutical industry.
American Jobs and Operations
- Biopharmaceutical workers are employed at more than 1,500 manufacturing facilities across 47 states, the District of Columbia and Puerto Rico
- Six states — California, Massachusetts, New Jersey, New York, North Carolina and Pennsylvania — each have more than 50,000 workers directly employed by the biopharmaceutical industry.
- 24 states and Puerto Rico have an industry workforce exceeding 10,000 jobs.
- Six states have between 5,000 and 10,000 people in biopharmaceutical industry jobs.
- Compensation averages $157,712 annually per worker directly employed by the biopharmaceutical sector, more than twice the national average across all industries.
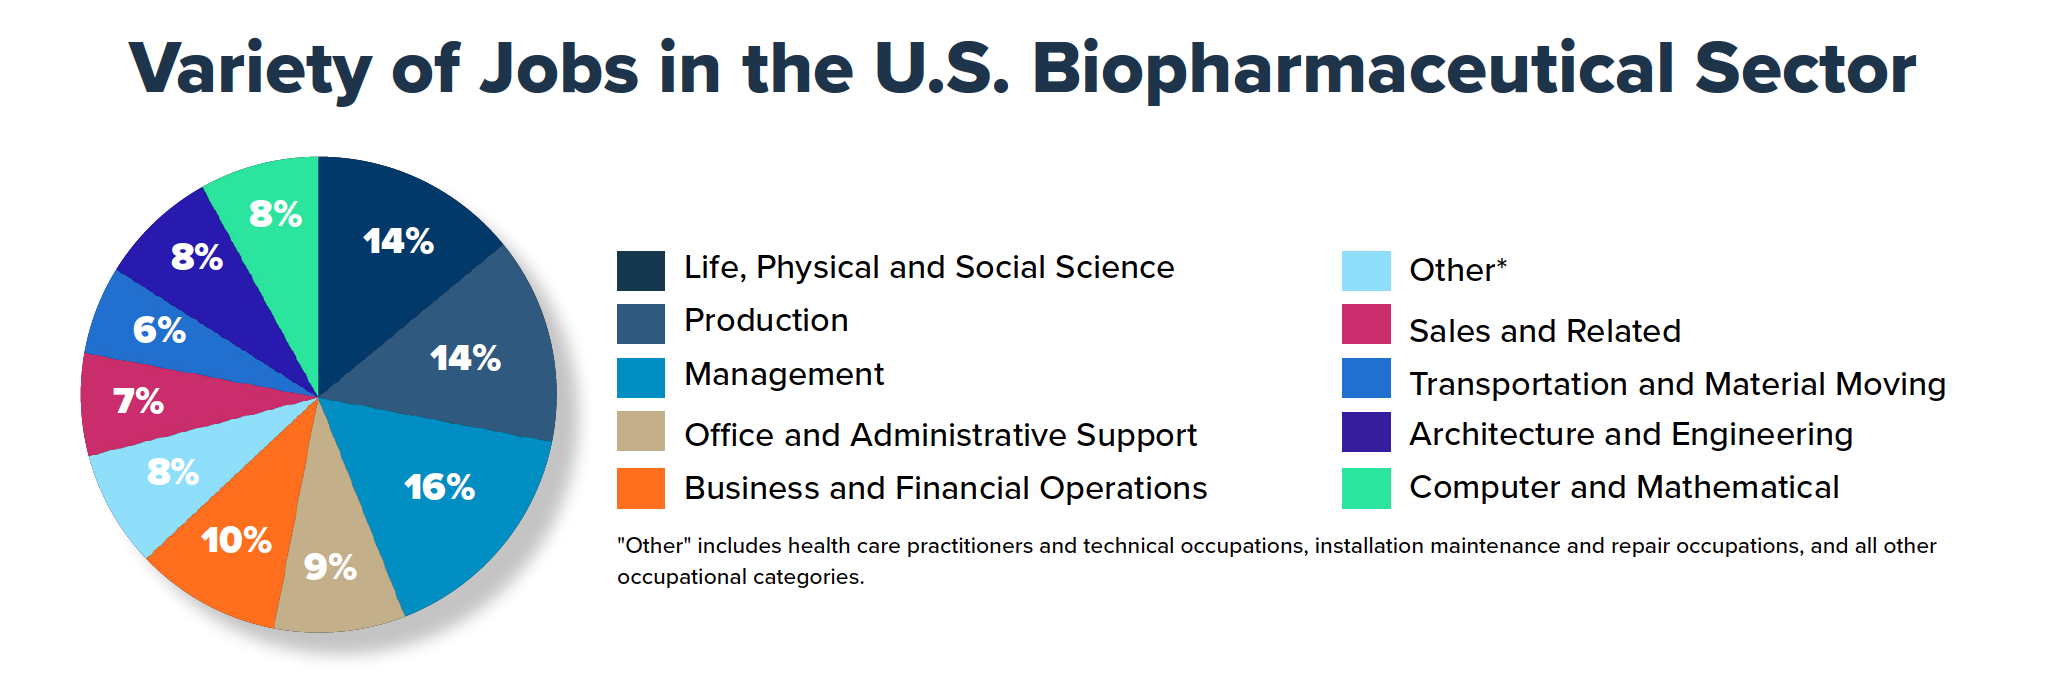
To learn more about your state, visit our PhRMA.org/States.
Tim McClung
Biopharmaceutical industry supports jobs and drives economic growth across the United States
Government price-setting boards: Why Minnesota needs to take a better approach
Lawmakers in numerous state capitals — including Minnesota — continue to debate reforms intended to lower the cost of prescription drugs for patients. We agree, out-of-pocket costs for patients are too high. As we’ve said before, patients need help affording their medicines. Unfortunately, organizations backed by the insurance industry — have lobbied for state lawmakers to embrace so-called prescription drug affordability boards. It’s no surprise that their path provides government bureaucrats the power to set prices for innovative medicines without addressing insurer and PBM roles in determining prescription drug costs.
Here are a few reasons why government price-setting boards will not help Minnesotans and remain unproven in other states across the country:
- Threaten the development of new medicines. Government price setting could result in fewer cures and treatments. For example, the Inflation Reduction Act’s (IRA) government price setting provisions are already impacting R&D decisions in harmful ways. But you don’t have to take our word for it. Minnesota Oncology — a leading provider of cancer care — warned that a state board could “prevent lifesaving and life-altering drugs from ever coming to market, reducing patient access to current and future treatment.”
- Fail to deliver lower costs to patients. States like Maryland and Colorado have already spent years trying to establish government boards with little to show for their efforts. These states have spent millions of dollars standing up handpicked bureaucrats, yet so far, they haven’t delivered any savings to date for patients at the pharmacy. Instead, for example, concerns about inaccurate data and questions about a state’s ability to implement price limits have plagued Colorado board members.
- Give a free pass to middlemen and health insurers. There is growing recognition that abusive practices by pharmacy benefit managers (PBMs) and health insurers are making medicines unaffordable. PBMs — and any health insurers that own one — reap large profits by shifting higher costs onto patients. Experts have warned that PBMs may prefer medicines with higher prices over lower cost alternatives because they may make more money, and they often refuse to share rebates and other savings directly with patients. Government boards let middlemen off the hook, ignoring the reasons why patients often can’t afford their treatments.
- Jeopardize patient access to lifesaving treatments. Government price setting allows unelected bureaucrats to come between patients and their medicines, threatening access to lifesaving care. For example, the IRA is hurting the ability of seniors to access their medicines under Medicare. This reaffirms previous research that found the IRA’s price setting scheme is jeopardizing seniors’ access to treatment options.
There are better ways to lower the cost of prescription drugs that protect access to medicines and the development of new treatments. For example, states can follow the lead of Arkansas and West Virginia, which now require insurers and PBMs to share savings with patients at the pharmacy counter.
To learn more about solutions lawmakers can pursue to lower costs and increase health care access, visit PhRMA.org/States.
Reid Porter
Government price-setting boards: Why Minnesota needs to take a better approach
Insurance data: PBM reform has no material impact on premiums
A first-of-its-kind analysis found no evidence a new law requiring insurance companies and their pharmacy benefit managers (PBM) to share rebates with patients has an impact on premiums.
Policymakers across the country are working to make sure patients don’t pay more for their medicines than insurers and PBMs.
Of course, the PBM industry and its insurance allies are doing everything they can to block this reform and others. They’re using old scare tactics and claiming that sharing savings with patients will force insurance premiums to increase.
As this analysis shows, the insurance industry’s own data debunk this all-too-common myth.
The problem.
People often pay more for medicine than their insurance company pays. Even though PBMs negotiate significant rebates that lower what health plans pay for medicines, they don’t have to share these savings with patients at the pharmacy counter. Instead, they often use rebates to subsidize insurance coverage for healthy individuals, while forcing those who need medicines to pay high costs.
This isn’t how insurance is supposed to work, and it’s one of many PBM abuses that lawmakers across the country are working to address.
The solution.
In addition to Arkansas, West Virginia and Indiana also require that rebates go directly to reducing patient costs at the pharmacy counter. Policymakers in other states and Congress are considering similar changes.
The new analysis by Milliman examined changes in premiums after Arkansas adopted a law requiring that rebates be shared with patients. The health care analytics firm reviewed annual rate filing information submitted by health plans to state regulators. What did they find? Not much. According to Milliman’s report:
“We did not find evidence in rate filing documents that the Act had a material impact on premium rate increases for Arkansas.”
The findings reaffirm other research that has shown sharing rebates directly with patients would have minimal impact on premiums. But the savings can be huge for some patients. This is certainly welcome news for people who need lifesaving cures and treatments, and it’s welcome news for lawmakers pushing this reform forward, even in the face of myths and scare tactics.
We know PBMs will put profits before patients. They’ve said as much in the past. Lawmakers need to put patients over PBMs by passing strong reforms that hold these middlemen accountable and lower what patients pay for medicines at the pharmacy counter.
To learn more visit PhRMA.org/States.
Nick McGee
Insurance data: PBM reform has no material impact on premiums
Government price setting won’t help patients in Illinois
While Illinois lawmakers consider a “Health Care Availability and Access Board” (sometimes referred to as a prescription drug affordability board or PDAB), these boards are really code for government price-setting. Illinoisans should be concerned.
Patients in Illinois face high health care costs and coverage barriers, but a price-setting board like the one proposed in HB 4472 is not the solution.
Here’s why:
- Government price-setting could limit access to critical medicines by inserting bureaucrats between patients and doctors.
- Insurance companies and pharmacy benefit managers (PBMs) are not currently required to share the discounts and rebates provided by biopharmaceutical manufacturers directly with patients. This bill does not address this issue.
- PBMs and their health insurance companies control what patients pay out-of-pocket, not manufacturers.
- Similar policies at the federal level (like the Inflation Reduction Act) — already jeopardize the development of new medicines — and these boards could have similar negative effects.
- There’s no system for checks and balances. Proponents of the board haven’t articulated how they will monitor and track alleged savings in any state.
PDABs in Maryland and Colorado are spending millions of dollars creating new bureaucratic positions and red tape — without helping one patient or saving one cent since 2019. Illinois shouldn’t be another open checkbook along the way to waste funds on misguided schemes.
Several patient groups across the country have publicly shared their concern that PDABs may reduce access to medicines. And they’ve been joined by voices across the supply chain including hospitals, insurers, and doctors. These voices expose real and unfortunate potential consequences to government price-setting and the establishment of these boards.
Patients need real leadership from everyone involved in our health care system to make it better. That’s why our companies are calling for policymakers to join us in supporting common-sense reforms to make insurance work like it was intended and help make sure patients can access and afford the medicines their doctors prescribe. For more information on the harm these boards cause and other solutions lawmakers can pursue to lower costs and increase health care access, visit PhRMA.org/States.
Stami Williams
Government price setting won’t help patients in Illinois
Colorado is proof: Too many unanswered questions remain about state government price setting's impact on patients and providers
As the Colorado Prescription Drug Board continues its affordability reviews, too many crucial issues remain unsolved. Beyond the persistent questions about methodology, data and process that we’ve discussed before, the entities responsible for implementing an upper payment limit (UPL) — insurers, hospitals, health care providers and pharmacies — have questioned whether they are even capable of doing it.
Several organizations vital to the healthcare system have voiced serious concerns about the board’s price-setting measures. But they are falling on deaf ears. Instead, the board’s decisions appear to ignore the anticipated consequences of their actions throughout the provider and supply chains as the flawed process moves forward. In fact, in public comments made during Colorado drug board meetings:
Insurers have pointed to barriers to implementation within plan design and claims systems.
- “[The Colorado Association of Health Plans] has concerns about the ability of health insurance carriers to alter their drug formularies so that individual drugs can be removed to align with an established UPL as well as changing claims systems to allow for single copay amounts specific to one drug… The uncertainty and costs associated could well outweigh the potential cost savings.” The Colorado Association of Health Plans (CAHP)
Hospitals have shared concerns about purchasing UPL drugs within their current purchasing model.
- “Colorado hospitals are concerned about any potential impact on the purchase price of national organizations as the majority of Colorado hospitals are members of Group Purchasing Organizations (GPOs) which allow hospitals to band together and realize savings through economies of scale on everything from prescription drugs to personal protective equipment to cleaning supplies. It is also important to note that GPOs are national in scope and not subject to Colorado law.” Colorado Hospital Association (CHA)
Providers have questioned how a UPL will work under their acquisition and reimbursement models and warn that a UPL will hurt their ability to stay afloat, drive up costs and endanger patients’ access to medicines.
- “As is the case for many complicated medications, there are numerous associated resources necessary in the process. If the health-system/pharmacy is not appropriately compensated for the entire process of supplying UPL medications, the only course of action is to absorb the cost and lose money, or, choose not to lose money and therefore ultimately choose not to stock the medication.” Colorado Pharmacists Society. Comment Letter. January 12, 2023
- “Not only would an Upper Payment Limit policy impact the providers ability to offer lower-cost prescription drug administration in a safe and controlled environment, but it would also increase the risk of forcing patients into a care setting the ultimately is more expensive for everyone.” Association of Women in Rheumatology (AWIR)
This political exercise already costs millions of dollars for the state without saving a dime for patients to date, and these statements only add to concerns that the board is rushing towards disastrous outcomes for patients who rely on life-saving medicines prescribed by their doctors. Colorado and other states should focus on the root cause of the affordability and accessibility problems: health insurance practices and the self-serving actions of the pharmacy benefit manager middlemen who control — and too often increase — costs at the pharmacy counter.
Reid Porter
Colorado is proof: Too many unanswered questions remain about state government price setting's impact on patients and providers
The truth about Nebraska's price setting push
As Nebraska lawmakers consider consider Legislative Bill 833, a proposal to create a so-called “prescription drug affordability board,” it’s important to know the truth about how government price setting will affect Nebraskans. A price-setting board could limit access to critical medicines while inserting the government between patients and doctors.
A recent poll found that 83% of adults in Nebraska agree that elected officials should ensure health insurance companies and pharmacy benefit managers (PBMs) are held accountable for their role in keeping patients from the medicines they need.
MYTH: A PDAB will help Nebraskans.
FACT: A Nebraska PDAB would stand between patients and doctors and decide which medicines are “worth” covering. This legislation would allow an unelected board to set an upper payment limit (UPL) – or price cap on all purchases and payer reimbursements of medicine dispensed or administered to individuals in the state. Regulating drug prices could lead to a shortage of or limit access to medicines for patients. Research shows that “[i]t is simply not true that government can impose significant price controls without damaging the chances for future cures.”
To date, there has been no real-world evidence to show that an upper payment limit actually benefits patients at the pharmacy counter. This legislation could leave hospitals, pharmacies, infusion clinics, and other health care providers with substantial costs that could impact patient access to needed treatments.
MYTH: A PDAB would finally address health concerns in Nebraska.
FACT: The current PDAB proposal fails to address the root problems patients face —health insurance companies and their PBM middlemen, who decide how much patients must pay at the pharmacy counter and are making it increasingly more difficult for patients to get the medicines they need. It doesn’t account for rising copays, deductibles, and coinsurance.
MYTH: A PDAB would save Nebraskans money.
FACT: Nebraska would have to foot the bill for an expensive PDAB if passed. Maryland has spent millions of dollars on its PDAB since 2019 with no evidence of lowering patient costs. PDABs also fail to address the real reason for rising costs: health insurance companies and PBMs.
MYTH: Biopharmaceutical manufacturers are needlessly pointing fingers at health insurers and PBM middlemen.
FACT: Manufacturers offer rebates and steep discounts that PBMs are not always passing to patients directly. Manufacturers also offer patient assistance for patients without insurance or to close the gap where insurers fail. It’s PBMs that decide what medicines patients can get and what people pay out-of-pocket, and in some cases, patients are paying the undiscounted price while the insurer and their PBM keep the savings.
MYTH: A PDAB and strong research and development in Nebraska can exist at the same time.
FACT: Government price controls, as the industry continues to be tirelessly dedicated to finding treatments and cures, divert resources elsewhere and could have chilling effects on research and development of new medicines.
MYTH: Nebraska legislators have identified a way to track and ensure savings for consumer out-of-pocket costs.
FACT: Lawmakers have yet to articulate how they will monitor and verify alleged savings for consumer out-of-pocket costs reported by plans. Many questions remain unanswered, and Nebraskans may need to brace themselves for following in the footsteps of Colorado and Maryland who have spent millions of dollars without saving patients a dime.
For more information on the harmful consequences of legislation like LB 833 and policies state lawmakers can pursue to lower costs and increase access, visit phrma.org/states.
Reid Porter
The truth about Nebraska's price setting push
ICYMI: Scott LaGanga and Matt Salo deliver a State of the Industry Report
We need to improve access to medicines and address patient affordability challenges across the United States.
Last month, I spoke with Matt Salo about this at Informa’s Medicaid Drug Rebate Program Summit. Matt — who is the founder and CEO of Salo Health Strategies and former executive director of the National Association of Medicaid Directors (NAMD) — and I examined the current state of Medicaid and our broader health care system. We also dove into patient access issues at both the state and federal level, including the ways that the government is inserting itself between patients and doctors beyond Medicaid.
During the discussion, I spoke to several solutions to improve access to medicines and reduce out-of-pocket costs.
- Share the savings: In states like Indiana and Arkansas, laws have passed that require insurers and their Pharmacy Benefit Managers (PBMs) to share the discounted price that they get with patients at the pharmacy counter. As more states adopt this model, we’ll see more savings go to patients rather than middlemen. No one should pay more for their medicine than their insurer – that is not how health insurance is supposed to work.
- Make patient assistance programs count: Ensuring the assistance that manufacturers provide to patients count towards deductibles and other cost-sharing requirements is one step forward in increasing access. These programs exist to support people without insurance or when existing commercial coverage fails, increasingly a result of abusive insurance benefit design. Nearly twenty states have already passed policies to guarantee that patients see the full benefit of discount programs intended to help them afford their medicines. Assistance programs would rarely be needed if insurers provided adequate coverage in their formularies.
- Hold PBMs accountable: PBMs continue to game the system for their own benefit at the expense of patients. State policymakers can hold PBMs accountable and address abuses in the system that are making it harder for patients to get the medicines they need.
Click the image below to watch our conversation, and learn more at phrma.org/middlemen.

Scott LaGanga
ICYMI: Scott LaGanga and Matt Salo deliver a State of the Industry Report
4 truths about state government price setting
What you should know
Groups motivated by special interests (see NASHP) and backed by insurance companies (see AARP) are pushing states to adopt flawed price-setting schemes, often in the form of prescription drug affordability boards (PDABs). Establishing these boards wedges government-appointed bureaucrats between doctors and their patients while shortsightedly focusing on only one component of health care — all too curiously avoiding any review of or actions on abusive health insurance practices. This is not good news for patients.
The truth is that PDABs:
- Risk patients’ access to medicines. Prescription drug boards are government price setting schemes that let politicians set medicine prices with little accountability to, or input from, patients and their doctors. Under this scheme, an unelected board of bureaucrats evaluates the price of medicines and determines whether certain medicines and treatments are worth paying for, with the state coming between patients and the treatments their doctors prescribe.
- Reduce predictability for patients. Too many unanswered questions remain. What happens if a drug becomes unobtainable at the board’s arbitrarily set price, or board decisions result in reduced treatment options for patients? Or, what happens if middlemen reduce health insurance coverage for the non-price-controlled drugs that patients still need?
And that’s not all. Politically appointed boards like these take control away from patients and their doctors, leaving the access and affordability of life-saving medicines in the hands of each election cycle. - Ignore the true reasons for high patient out-of-pocket costs. These boards fail to address the root problems facing patients — abusive practices of pharmacy benefit managers (PBMs). Too often, health insurers and PBMs:
- use harmful tactics, like accumulator adjustment and co-pay maximizer programs, to deny patients benefits of patient assistance programs.
- use utilization management tools, like requiring prior authorization or failing first on other therapies, which can create significant barriers between patients and the medicines their doctors prescribe.
- choose to pocket the tens of billions in rebates and discounts they receive on medicines for their own profit instead of sharing the savings with patients.
- Jeopardize development of new medicines. We are already seeing the impacts of price-setting policies at the federal level (Inflation Reduction Act), and state boards could have similar effects:
- Government price setting policies reduce biopharmaceutical companies’ ability to invest in the post-approval research required to see if they can be used in new ways, especially in disease areas like cancer.
- Analysis shows investments in research and development are already shifting away from small molecule medicines (pills and tablets) because of the IRA’s “pill penalty,” despite the benefit these types of medicines have for patients.
- One manufacturer has made clear they are “not going to do certain [clinical] trials … because it is becoming financially not viable [due to the IRA].”
- Government price setting policies reduce biopharmaceutical companies’ ability to invest in the post-approval research required to see if they can be used in new ways, especially in disease areas like cancer.
Patients deserve better. Instead of adopting flawed price-setting schemes, states should implement common-sense reforms to make insurance work like insurance to safeguard patient access and affordability for the medicines their doctors prescribe.
Reid Porter
4 truths about state government price setting
Three concerns about Colorado's approach to government price setting
After roughly $2 million, several years and the use of flawed data, Colorado is now enabling unelected bureaucrats to set medicine prices through its so-called “Prescription Drug Affordability Board” (PDAB). Other states should look to Colorado as a warning for three key reasons.
1. Concerns are growing over the board’s purported “methodology” and data bias.
- The PDAB’s so-called “methodology” is prone to error. For example, the board had to rework its method for calculating the cost of a “course of treatment,” affecting its initial determinations for the list of eligible drugs.
- Even during the board discussion that led to the selection of drugs, questions arose over the accuracy of the data available for the number of Colorado patients using a particular drug. Despite this concern, the board still used patient count as a major determining factor in selecting drugs for affordability review.

2. Colorado’s PDAB is using an incomplete database to make decisions about the price of medicines.
- The claims data being used by the PDAB represents less than 70% of Coloradans and less than 75% of insured individuals in the state, providing an incomplete picture for decision making.
- The claims data used by the PDAB does not consider how insurance benefit design impacts out-of-pocket costs for insured Coloradan. For example, the database omits information such as whether a patient has coinsurance or a high deductible health plan. Omitting this information paints an incomplete picture because it ignores the fact that insurers and their pharmacy benefit managers are increasingly shifting more costs to patients through high deductibles and coinsurance.
- The database being used does not account for available rebates, discounts and other price reductions that Medicaid and private health insurers receive from pharmaceutical companies. This means the PDAB made decisions about the drugs to review based on amounts other than what Medicaid or health insurers actually paid.
3. The PDAB is rushing the process. Colorado’s law has no statutory deadline for selecting drugs for affordability reviews. Given the concerns and questions raised surrounding their methods, scope and the accuracy of the data they are relying on, rushing the process does not benefit patients.
Who is, and is not, on Colorado’s PDAB?
- Who’s on: Former insurance company and hospital executives.
- Who’s not: Patients or patient representatives, even though patients will be most impacted by the board’s decisions. And employees or representatives of the biopharmaceutical industry – which researches, develops and manufacturers life-saving medicines – are statutorily excluded from sitting on the board.

Coloradans deserve better.
Policymakers in Colorado have created a system in which patients may face significant barriers to lifesaving medicines because of government price setting. Coloradans should demand that state lawmakers address these concerns before the PDAB makes any further decisions.
Learn about better ways to help patients pay less for their medicines without using politically-appointed government boards to make decisions that are better left between patients and their doctors at PhRMA.org/States.
Reid Porter
Three concerns about Colorado's approach to government price setting
Michigan proposal jeopardizes access to medicines
Michigan politicians are considering creating a “board” of people – picked by state politicians – that would institute government price-setting for medications in ways that will likely have long-term, harmful effects on access and the development of new, life-saving therapies. While these legislators may be well-intentioned, this disruptive approach completely misses the mark.
Here’s what you need to know:
- Referred to as a “prescription drug affordability board,” what this proposal really does is put the government between patients and their doctors.
- The legislation would create a board that is subject to the whims of politics and special interests, not the best interests of patients.
- The proposal also fails to address the root problems facing patients – the health insurance companies and pharmacy benefit middlemen that make it harder for people to get the medicines they need.
Patients need better access and affordability when it comes to their medicines, not an unelected board of government bureaucrats making decisions about their medicine’s value.
What can be done
Michigan deserves an honest discussion about affordable medicines.
Legislators looking for ways to help their constituents can start by making concrete changes that lower what people pay for medicines at the pharmacy counter without creating more barriers and threatening access to care. That means:
- Making sure no patient is paying more for their medicines than their health insurance company or pharmacy benefit manager (PBM).
- Protecting cost-sharing assistance for people who need help accessing and affording their medicines.
- Holding middlemen accountable for business practices that line their pockets at the expense of the patients they are supposed to serve.
To learn more visit phrma.org/states.
Stami Williams
Michigan proposal jeopardizes access to medicines
A win for Indiana patients: “Sharing the savings” legislation now law
Indiana just joined West Virginia and Arkansas in delivering an important win for Hoosiers who are struggling to afford their medicines. This week, Governor Holcomb signed into law Senate Bill 8 recently passed by the Indiana legislature. This new law will ensure that Indiana patients aren’t paying more for their medicines than their health insurance company or the middlemen known as pharmacy benefit managers (PBMs).
This concept, known as “share the savings,” puts money back in patients’ pockets by requiring insurers and the PBMs they work with to share the rebates, discounts, and other price concessions they receive from manufacturers directly with patients at the pharmacy counter.
Negotiations between pharmaceutical companies, health insurers, PBMs and others result in significant rebates and discounts that totaled $236 billion in 2021. However, those savings aren’t always shared with patients, which means there are patients who end up paying more for their medicine than their insurer and PBM. This legislation requires 85% of the rebates health insurance companies receive from manufacturers be applied to lower drug costs for patients at the pharmacy counter in Indiana’s individual market and requires insurers to pass through 100% of rebates to plan sponsors (employers) in the fully insured group market, which employers can decide how to share with enrollees. This means lower out-of-pocket costs for Hoosiers, as well as an increased likelihood of better health outcomes as more people will take their medicine as prescribed.
A recent 50-state poll conducted by Morning Consult on behalf of PhRMA found that strong majorities in every state, including Indiana, agree lowering out-of-pocket costs for health care should be a top policy priority. Specifically:
• 80% of adults in Indiana support a law that would prevent patients from paying more for their prescription medicine than their insurance company or pharmacy benefit manager (PBM).
• 82% of respondents in Indiana agreed elected officials should ensure health insurance companies and middlemen are held accountable for their role in keeping patients from the medicines they need.
Indiana patients should have access to affordable medicines, and this legislation is a significant step toward achieving that goal.
To learn more, visit PhRMA.org/States.
Reid Porter
A win for Indiana patients: “Sharing the savings” legislation now law